
The Perimenopause Patient: Who She Is and Why Conventional Care Failed Her
The Patient Profile and Consultation Framework That Determines Whether Your Clinic Converts Her
She Has Already Been Dismissed at Least Once
This is the single most important thing to understand about the patient a women's hormone clinic serves. By the time she books a consultation, she has usually already raised her symptoms with a physician and come away without a satisfying answer.
She may have been told her labs were normal, with no one looking further into her symptoms. She may have been offered an antidepressant for mood symptoms with a hormonal driver. She may have been told that what she is experiencing is a normal part of aging and left at that.
The scale of undertreatment is documented: in 2020, about 41 million U.S. women were ages 45 to 64, yet only about 2 million women ages 46 to 65 received a hormone therapy prescription, according to the FDA's February 2026 announcement.
In the FDA's words, just "a small fraction of women who could benefit from these treatments" are using them.
For the market and the steps to open one, see how to open a women's hormone clinic.
The WHI Legacy She Is Carrying
Clinics serving this population need to understand the history their patients arrive with, because it shapes the conversation whether the clinic raises it or not.
After the Women's Health Initiative study, the FDA applied boxed warnings to hormone therapy in the early 2000s, and hormone therapy use plummeted, according to HHS's November 2025 announcement. A generation of women and their physicians absorbed the message that hormone therapy was dangerous.
Subsequent analysis by age and time since menopause substantially revised that picture, and the FDA has now acted on it: in February 2026 it approved label changes removing the cardiovascular disease, breast cancer and probable dementia risk statements from the boxed warning of the first six products, and it noted that randomized studies show reductions in all-cause mortality and fractures among women who start hormone therapy within 10 years of menopause onset, generally before age 60.
The practical consequence for a clinic is that many patients hold a risk perception formed more than two decades ago from evidence that has since been reinterpreted. Correcting that accurately, without overcorrecting into claims the evidence does not support, is a core clinical communication task in this category.
What She Is Actually Experiencing
According to the HHS Office on Women's Health, perimenopause usually begins in a woman's mid- to late 40s and lasts about four years on average, though it can last up to 10 years. The symptom picture is often broader than patients expect, and broader than a general practice visit usually allows time to explore.
•Vasomotor symptoms: hot flashes and night sweats, which can persist for years
•Sleep disruption, frequently the symptom that finally prompts her to seek care
•Cognitive changes: word-finding difficulty and concentration lapses she may fear indicate something worse
•Mood changes, often misattributed to primary depression or anxiety
•Genitourinary symptoms: vaginal dryness, discomfort, urinary changes, which she may not volunteer unless asked directly
•Body composition changes that do not respond to what previously worked
Two of these deserve particular operational attention. Cognitive symptoms often carry disproportionate fear, so naming them as a recognized part of the transition can be a genuine relief. Genitourinary symptoms are frequently underreported because patients do not raise them spontaneously; a structured intake that asks directly surfaces a problem the medical director can then evaluate. Some founders build a whole practice around sexual health concerns like these; see what it takes to open a women's sexual health clinic.
The Consultation Framework That Earns Her Trust
The conversion mechanism in this category is not persuasion. It is thoroughness, because thoroughness is precisely what she has not received.
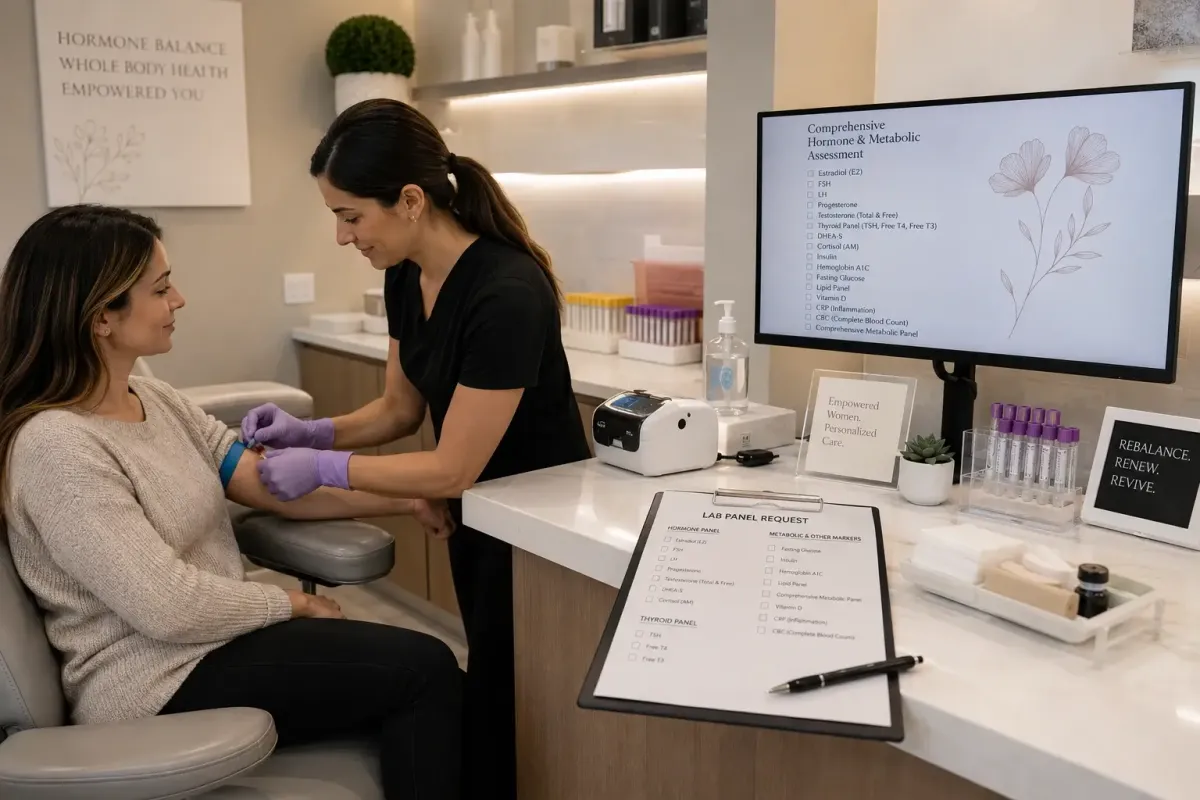
Open with a structured symptom history that covers the full range above, including the ones patients do not volunteer. When the medical director orders a comprehensive panel, the clinician explains what each marker assesses and why, then reviews the results with her directly, connecting specific findings to specific symptoms she described.
The moment that earns her trust is often the same: she sees objective data that corresponds to what she has been experiencing, presented by someone who took the time to look properly. That is the entire proposition. A clinic that leads with a product or a pellet program before that clinical foundation is in place risks losing her at that point.
Where the medical director's evaluation warrants it, the honest answer sometimes includes that hormone therapy is not the right intervention, or not the only one. Thyroid dysfunction, iron deficiency, and sleep disorders can all produce overlapping symptoms. A clinic willing to say so earns the kind of trust that leads to referrals.
What Keeps Her Enrolled
Acquisition in this category can be comparatively straightforward given the unmet demand. Retention is where clinics separate.
The mechanism is the one that drives retention in many hormone practices: objective data showing change. A patient who sees her labs and her symptom scores change across reviews, on the schedule the medical director sets, has evidence of how the program is working for her. That evidence can sustain enrollment through the months when she feels little change.
What is distinctive here is the value of tracking symptoms formally alongside labs. Many of the changes she cares most about (sleep quality, cognitive clarity, mood stability) do not appear on any panel. A clinic that captures them with a structured symptom inventory at each review can show progress that bloodwork alone would miss, and can flag a regression early enough for the medical director to adjust the protocol.
The other retention factor is continuity. This patient's entire complaint about prior care is that nobody followed through. Seeing the same clinician across visits, who remembers her history without rereading the chart, is not a luxury in this category. It is the core of the product.
The Testosterone Conversation
Many of these patients ask about testosterone, usually regarding libido, energy, or muscle mass. Clinics should be prepared to discuss it accurately.
There is no U.S.-approved testosterone product for women, so where testosterone therapy is provided, it is prescribed off-label. The only evidence-based indication for testosterone in women is hypoactive sexual desire disorder in postmenopausal women diagnosed after a formal biopsychosocial assessment, and there are "insufficient data" to make any recommendation for premenopausal women; prescribing an approved male formulation is "reasonable" when no approved female product is available, provided hormone levels stay in the female physiologic range; and compounded "bioidentical" testosterone "cannot be recommended" for that indication, according to a 2019 global consensus statement endorsed by the Endocrine Society. Testosterone is also Schedule III, which brings DEA registration into scope for a clinic that prescribes, dispenses or administers it.
The clinically honest framing is that testosterone for women is a legitimate but off-label intervention with a narrower evidence base than estrogen and progesterone therapy, appropriate in specific circumstances, at the medical director's discretion, and requiring monitoring. Clinics that present it as an established standard overstate the evidence. Clinics that refuse to discuss it lose patients to practices that will.
Where She Is and How She Finds You
This patient researches extensively before booking. She reads, listens to podcasts on the topic, and participates in online communities where midlife women's health is discussed candidly. She often arrives better informed than many cash-pay patients.
Local search reaches her at the decision point, when she looks for menopause specialists and hormone clinics in her area. Educational content that treats her as capable of understanding clinical detail tends to serve her better than marketing that speaks around the subject. ACG plans the menopause clinic marketing strategy. Marketing execution is a separate engagement.
Referral can be strong in this population. Women often discuss these symptoms with each other in ways that men generally do not discuss theirs, and a patient who values her care may tell the women in her circle who are going through the same transition.
If you are opening a clinic of your own, see how we launch a new clinic built around this patient; to discuss patient acquisition strategy for this population, book a free 30-minute strategy call.
Frequently Asked Questions
What age range should a women's hormone clinic target?
There is no fixed range. Perimenopause usually begins in a woman's mid- to late 40s and lasts about four years on average, according to the HHS Office on Women's Health. A clinic that markets only to postmenopausal women misses women in perimenopause, who can have symptoms for years before menopause itself.
How do I discuss the boxed warning change with patients?
Accurately and with appropriate specificity. In February 2026 the FDA approved the first label changes removing the boxed-warning risk statements on cardiovascular disease, breast cancer and probable dementia from menopausal hormone therapy, after asking 29 drug companies to revise their labels; that first batch covered six products, so more may follow. The boxed warning for endometrial cancer stays on systemic estrogen-alone products. Describing the change as a blanket removal of all warnings is inaccurate and undermines credibility.
Should marketing for this patient use the word menopause?
Yes. Avoidance reads as discomfort with the subject, which is exactly the dynamic this patient has encountered elsewhere. Direct, clinically literate language usually lands better than euphemism with a population that has grown tired of euphemism. Paid ads still follow each platform's health ad rules, and Meta restricts health and wellness ads.
What decides whether she enrolls after the consultation?
Usually whether she feels properly evaluated. A consultation that starts with a full symptom history and walks her through the results of the panel the medical director orders feels different from what she experienced before, and that difference, more than marketing spend or pricing, is what she is deciding on.
